OCD in children and adolescents is characterised by recurrent unwanted thoughts (obsessions) and repetitive behaviours or mental acts (compulsions) that the child feels compelled to perform. If untreated, paediatric OCD is associated with substantial functional impairment in academic, social and family domains and tends to persist into adulthood (Heyman et al., 2006). Reliable measurement of severity in young people is challenging because children may under-report or over-report their symptoms during clinical interview, and parents often have observable information about compulsions (washing, checking, ordering) that the child cannot articulate. A parent-report measure offers a useful complement to a child-report, particularly for younger children and for tracking change over time.
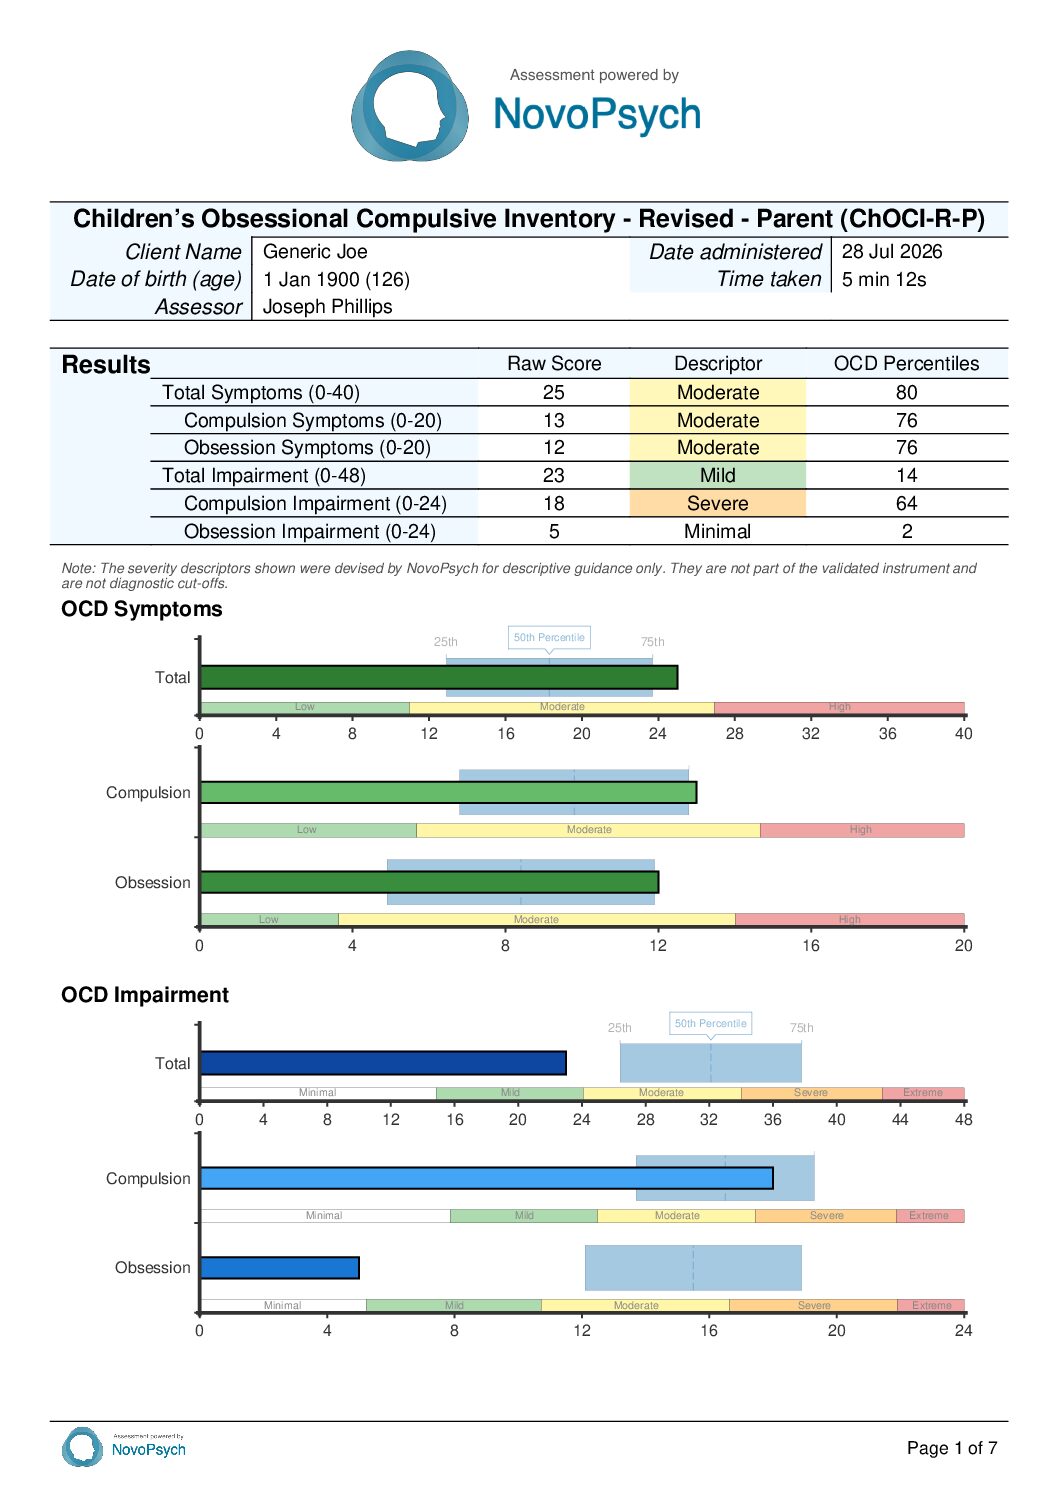
The ChOCI-R-P comprises six scored outputs across two construct dimensions:
Example ChOCI-R-P Item

The measure is designed for use with children and adolescents who have an established or suspected diagnosis of OCD. Its primary application is progress monitoring during treatment for paediatric OCD, where pre-treatment, mid-treatment and post-treatment scores can be compared to track symptom reduction and functional improvement. The subscale structure of the ChOCI-R-P can also guide where a clinician focuses exposure hierarchies and cognitive intervention. Additionally, the measure can inform formulation, where the symptom and impairment profile contributes to a broader case conceptualisation alongside diagnostic interview and child-report data.
The ChOCI-R-P produces six raw scores by summing item responses. Higher scores indicate more obsessive-compulsive symptoms or greater associated functional impairment. The measure produces two parallel sets of scores: symptoms (how often and how strongly OCD presents) and impairment (how much OCD disrupts daily life).
Six open-text items (items 11 to 13 for habits and items 30 to 32 for thoughts) ask the parent to describe the child’s three most upsetting habits (compulsions) and thoughts (obsessions), respectively. These items are not scored, but provide additional clinical information to inform assessment and treatment planning.

Each raw score is presented alongside a percentile rank against an OCD-clinical reference sample (Uher et al., 2008). A percentile of 50 corresponds to the OCD-clinical reference average; a percentile of 80 indicates a score exceeding approximately 80% of OCD-diagnosed children in the reference group. Because the reference sample is clinical (not community), percentile interpretation is positional within an OCD-diagnosed group: a percentile of 50 reflects the average level for a child diagnosed with OCD, not the general paediatric population.
Each of the six scores is reported with a severity descriptor alongside its percentile. The descriptors are a descriptive guide, not diagnostic cut-offs, and do not replace clinical judgement.
Symptoms (three bands): A Low label (green) indicates a symptom level lower than typical for children with OCD (atypically light for this reference group); Moderate (yellow) indicates a symptom level within the typical range for children with OCD; High (red) indicates a symptom level above the typical OCD-clinical range. Each subscale has its own cut-offs, placed at the same position in the reference sample as the Total Symptoms cut-offs. Raw-score boundaries:
Impairment (five bands): A Minimal label (white) indicates functional disruption lower than typical for children with OCD; Mild (green) indicates mild functional disruption relative to the OCD-clinical reference; Moderate (yellow) indicates functional disruption within the typical OCD-clinical range; Severe (orange) indicates functional disruption in the middle-to-upper portion of the OCD-clinical reference distribution; Extreme (red) indicates functional disruption among the highest levels observed in the OCD-clinical reference distribution. Each subscale has its own cut-offs, placed at the same position in the reference sample as the Total Impairment cut-offs. Raw-score boundaries:
Each subscale assesses a different aspect of obsessive-compulsive symptoms or associated impairment. Higher scores on Compulsion Symptoms indicate that the parent has observed more frequent or more severe compulsive behaviours, including washing, checking, ordering, counting, repeating, and reassurance-seeking. Higher scores on Obsession Symptoms indicate more frequent intrusive thoughts of harm, contamination, doubt, mortality, blasphemy, or aggressive content. Higher scores on Compulsion Impairment indicate greater functional disruption from compulsions, including time spent, interference with school and friends, distress when prevented from acting, difficulty resisting or controlling compulsions, and avoidance. Higher scores on Obsession Impairment indicate similar impacts associated with obsessive thoughts.
When the ChOCI-R-P is administered on multiple occasions, change between administrations can be evaluated using a Reliable Change Index (RCI). A change of approximately 8.4 raw-score points or greater on Total Impairment, or 8.6 or greater on Total Symptoms, indicates a change that is unlikely to be attributable to measurement error alone.
On first administration, the report presents a results table followed by two construct sections (Symptoms and Impairment). Each section contains two horizontal raw-score charts. The first plots the construct’s total as a single bar with the client’s raw score against a 25th-to-75th percentile reference rectangle and a dashed line at the clinical average from the OCD-clinical reference sample. The second plots the construct’s two subscales (Compulsion and Obsession) with their own reference rectangles and clinical-average lines.


On repeat administration, the report presents the same results table followed by a 2×3 grid of multi-administration raw-score line plots organised by construct: top row Symptoms (Total, Compulsions, Obsessions); bottom row Impairment (Total, Compulsions, Obsessions). Each plot shows one score over time on its own descriptor bands, so the shading behind each point matches that score’s descriptor in the results table. Unlike the first-administration charts, these graphs emphasise longitudinal change rather than position within the clinical reference distribution.

The ChOCI-R has self-report and parent-report forms, developed and validated together (Uher et al., 2008); NovoPsych refers to them as the ChOCI-R-S and ChOCI-R-P, and ‘ChOCI-R’ below refers to the instrument as a whole or to findings covering both forms.
The ChOCI-R is a revision of the original CHOCI (Shafran et al., 2003), refined to improve item-level psychometrics and broaden severity coverage. The original CHOCI used 19 symptom items rated on a three-point scale (1 to 3) and a 10-item impairment scale derived from the CY-BOCS interview (Goodman et al., 1989; Scahill et al., 1997), scored 0 to 4. The ChOCI-R retains the 10 best-performing symptom items per section (compulsions and obsessions), changes the symptom response format to a three-option scale scored 0 to 2, and adds an avoidance item to each impairment section to align with the adult Y-BOCS. The remaining five impairment items (time, interference, distress, resistance, control) are unchanged between the original CHOCI and the ChOCI-R (Uher et al., 2008).
Published reports describe the ChOCI-R-P as a 32-item measure (the scored items only). NovoPsych’s version also administers six unscored open-text items describing the child’s worst habits and thoughts, which, like the Y-BOCS symptom checklist, capture specific symptom content to aid formulation, giving 38 items in total.
Psychometric validation of the ChOCI-R was conducted in a sample of 285 children and adolescents attending an OCD clinic over the period 2000 to 2006 (Uher et al., 2008). All children met ICD-10 criteria for OCD established via structured clinical interview.
Factor-analytic work supports the use of separate Compulsion and Obsession subscales for clinical interpretation. Exploratory analysis of the ChOCI-R-P recovered three factors broadly corresponding to Compulsions, Obsessions and Resistance, with the parent version showing less clean obsession/compulsion separation than the self-report version (Uher et al., 2008). This pattern is consistent with parents inferring obsessions from observed behaviours rather than directly accessing the child’s internal experience. The NovoPsych scoring approach prioritises the clinically meaningful distinction between compulsive and obsessive content, producing separate Compulsion and Obsession scores at both the Symptoms and Impairment levels.
Internal consistency of the ChOCI-R-P is strong across the four subscales and two totals (Uher et al., 2008). For the impairment scales, Cronbach’s α was .84 (Obsessions Impairment, N = 240), .78 (Compulsions Impairment, N = 269) and .87 (Total Impairment, N = 240). For the symptom scales, α was .86 (Obsession Symptoms, N = 240), .75 (Compulsion Symptoms, N = 269) and .85 (Total Symptoms, N = 240). The lower α for the Compulsion Symptoms scale reflects the heterogeneity of compulsive behaviours, with the hand-washing item showing a low item-total correlation; the authors retained the item to preserve coverage of a clinically common compulsion.
Convergent validity was demonstrated through a moderate correlation between the ChOCI-R-P Total Impairment and the CY-BOCS Total score (r = 0.45, N = 199, p < .001; Uher et al., 2008). The moderate (rather than strong) correlation, compared with r = 0.55 for the ChOCI-R-S against the CY-BOCS, reflects the partial independence of parent observation and clinician-rated severity in young people.
Inter-rater agreement between ChOCI-R-P and ChOCI-R-S was strong, with intraclass correlation coefficients of 0.77 (95% CI 0.69–0.83) for Total Impairment, 0.70 (95% CI 0.59–0.77) for Obsessions Impairment, and 0.80 (95% CI 0.74–0.85) for Compulsions Impairment (Uher et al., 2008).
Item-response theory (IRT) analysis demonstrated that the parent-report ChOCI-R-P provides better discrimination across the mild-to-moderate severity range than the CY-BOCS interview, which discriminates best at the most severe end of the spectrum (Uher et al., 2008). This complementary discriminatory profile supports the use of the ChOCI-R-P as a routine outcome measure in clinical practice, where many children present in the mild-to-moderate severity range and finer-grained discrimination is clinically useful.
The ChOCI-R-P has demonstrated sensitivity to change in three independent treatment studies spanning the paediatric age range (7 to 17). Lenhard and colleagues (2017) reported a within-group pre-post effect of d = 0.68 (95% CI 0.18–1.18) and a between-group effect of d = 0.59 (95% CI 0.09–1.10) favouring internet-delivered CBT over waitlist in adolescents aged 12 to 17 (N = 67; p = .012), with continued improvement to a 3-month follow-up. Aspvall and colleagues (2018) reported very large pre-post effects (d = 2.15, 95% CI 1.07 to 3.20) in a 12-week internet-delivered CBT open trial with young children aged 7 to 11 (N = 11), with α = .87 in that sample (replicating Uher et al., 2008). Chessell and colleagues (2024) reported large pre-post effects in a parent-led brief CBT case series of pre-adolescents aged 5 to 12 (N = 10): d ≈ −1.0 for symptoms and d ≈ −1.1 for impairment, with 50% reliable improvement on symptoms and 60% on impairment at post-treatment.
Each score is reported with a severity descriptor. The Total Impairment descriptors use the CY-BOCS severity bands (Goodman et al., 1989), converted to ChOCI-R-P scores using the table of equivalent scores in Uher et al. (2008). The Total Symptoms descriptors sit one standard deviation either side of the clinical mean in the same study. The lowest impairment band, called “subclinical” on the CY-BOCS, is labelled “Minimal” in NovoPsych because the reference sample is children attending an OCD clinic.
The descriptors are a descriptive guide, not diagnostic cut-offs, and do not replace clinical judgement. NovoPsych placed each subscale’s cut-offs at the same percentile as the matching Total cut-off, using each subscale’s own mean and SD from Uher et al. (2008), with each band starting at the next whole score. For symptoms, Moderate starts at about the 17th percentile and High at about the 85th. For impairment, Mild starts at about the 1st–2nd percentile, Moderate about the 16th, Severe about the 58th and Extreme about the 89th.
Note. The CY-BOCS severity bands (0–7, 8–15, 16–23, 24–31, 32–40) are widely used and are usually cited to Goodman et al. (1989), and sometimes to the CY-BOCS validation paper (Scahill et al., 1997). NovoPsych could not find them in either paper, in the scale authors’ later work, or anywhere else. We therefore treat them as an established clinical convention, and keep them for consistency with common practice and with earlier NovoPsych reports.
Reference percentiles are derived from Uher and colleagues (2008): 285 consecutive referrals (240 to 269 with complete parent-report data per subscale) to an OCD clinic between 2000 and 2006, all meeting ICD-10 criteria for OCD via structured clinical interview, with no significant sex differences (boys’ average age = 13.7, range 7 to 18; girls’ average age = 13.7, range 9 to 18). Reference parameters for the parent-report subscales are Compulsion Symptoms average = 9.8, SD = 4.5; Obsession Symptoms average = 8.4, SD = 5.2; Total Symptoms average = 18.3, SD = 8.0; Compulsion Impairment average = 16.5, SD = 4.2; Obsession Impairment average = 15.5, SD = 5.0; Total Impairment average = 32.1, SD = 8.4. Because this reference sample is clinical (not community), percentile interpretation is positional within an OCD-diagnosed reference group: a percentile of 50 reflects the average level for a child diagnosed with OCD, not the general paediatric population. No community-sample reference data exists for the parent-report ChOCI-R-P, and the original authors note that confirmation in primary care and population-based samples remains needed (Uher et al., 2008).